
Inseminación artificial
Back to back IUIs vs single any data from your clinic?



Timing matters for an IUI cycle, and the reassuring part is that the window is more forgiving than it can feel at 11pm while you are counting hours since an injection you gave yourself. Here is the full cycle timeline, when the trigger shot fits into it, and what the evidence actually shows about how much a few hours off really changes things.

An IUI cycle runs about four weeks, roughly one menstrual cycle. Monitoring begins in the first days, the trigger is given once the lead follicle reaches about 18 to 20 millimeters, insemination follows 24 to 36 hours later, and a pregnancy test is done about two weeks afterward.
Days 1 to about 5. Your cycle starts with a baseline appointment. If your cycle is stimulated, medication begins around this point; a natural cycle skips this step and moves straight to monitoring based on your own hormone rhythm.
Days about 6 to 11, the monitoring phase. Your clinic tracks follicle growth through a series of ultrasounds and blood draws, the number of visits depending on how your body responds and how your specific protocol is structured. This is the phase that determines exactly when the next steps happen, for every path to this cycle, whether you are doing IUI solo, with a partner, or with donor sperm, and it applies the same way for single mothers by choice as for anyone else moving through this same monitored process. Trans and AMAB patients undergoing IUI go through this same monitoring, adjusted to their own hormonal profile and protocol.
Days about 12 to 13, trigger and insemination. Once monitoring shows the lead follicle is ready, the trigger shot is given, and the insemination appointment itself is a brief procedure, scheduled a set number of hours afterward, covered in detail below. The insemination procedure itself takes about 5 to 10 minutes; sperm preparation in the lab typically runs 30 to 60 minutes beforehand, so plan for your full appointment time when scheduling.

Your body is one of a kind, and so is your treatment. Rely on a highly specialized medical team that explains your options with full transparency, backing every decision with precision technology and genuine, human support from day one.
Days about 14 to 28, luteal phase to pregnancy test. The two weeks after insemination is a waiting period that closes on the pregnancy test, when your clinic can give you an actual answer about the cycle. You can return to normal activities immediately after the procedure; the evidence does not support bed rest as improving IUI outcomes.
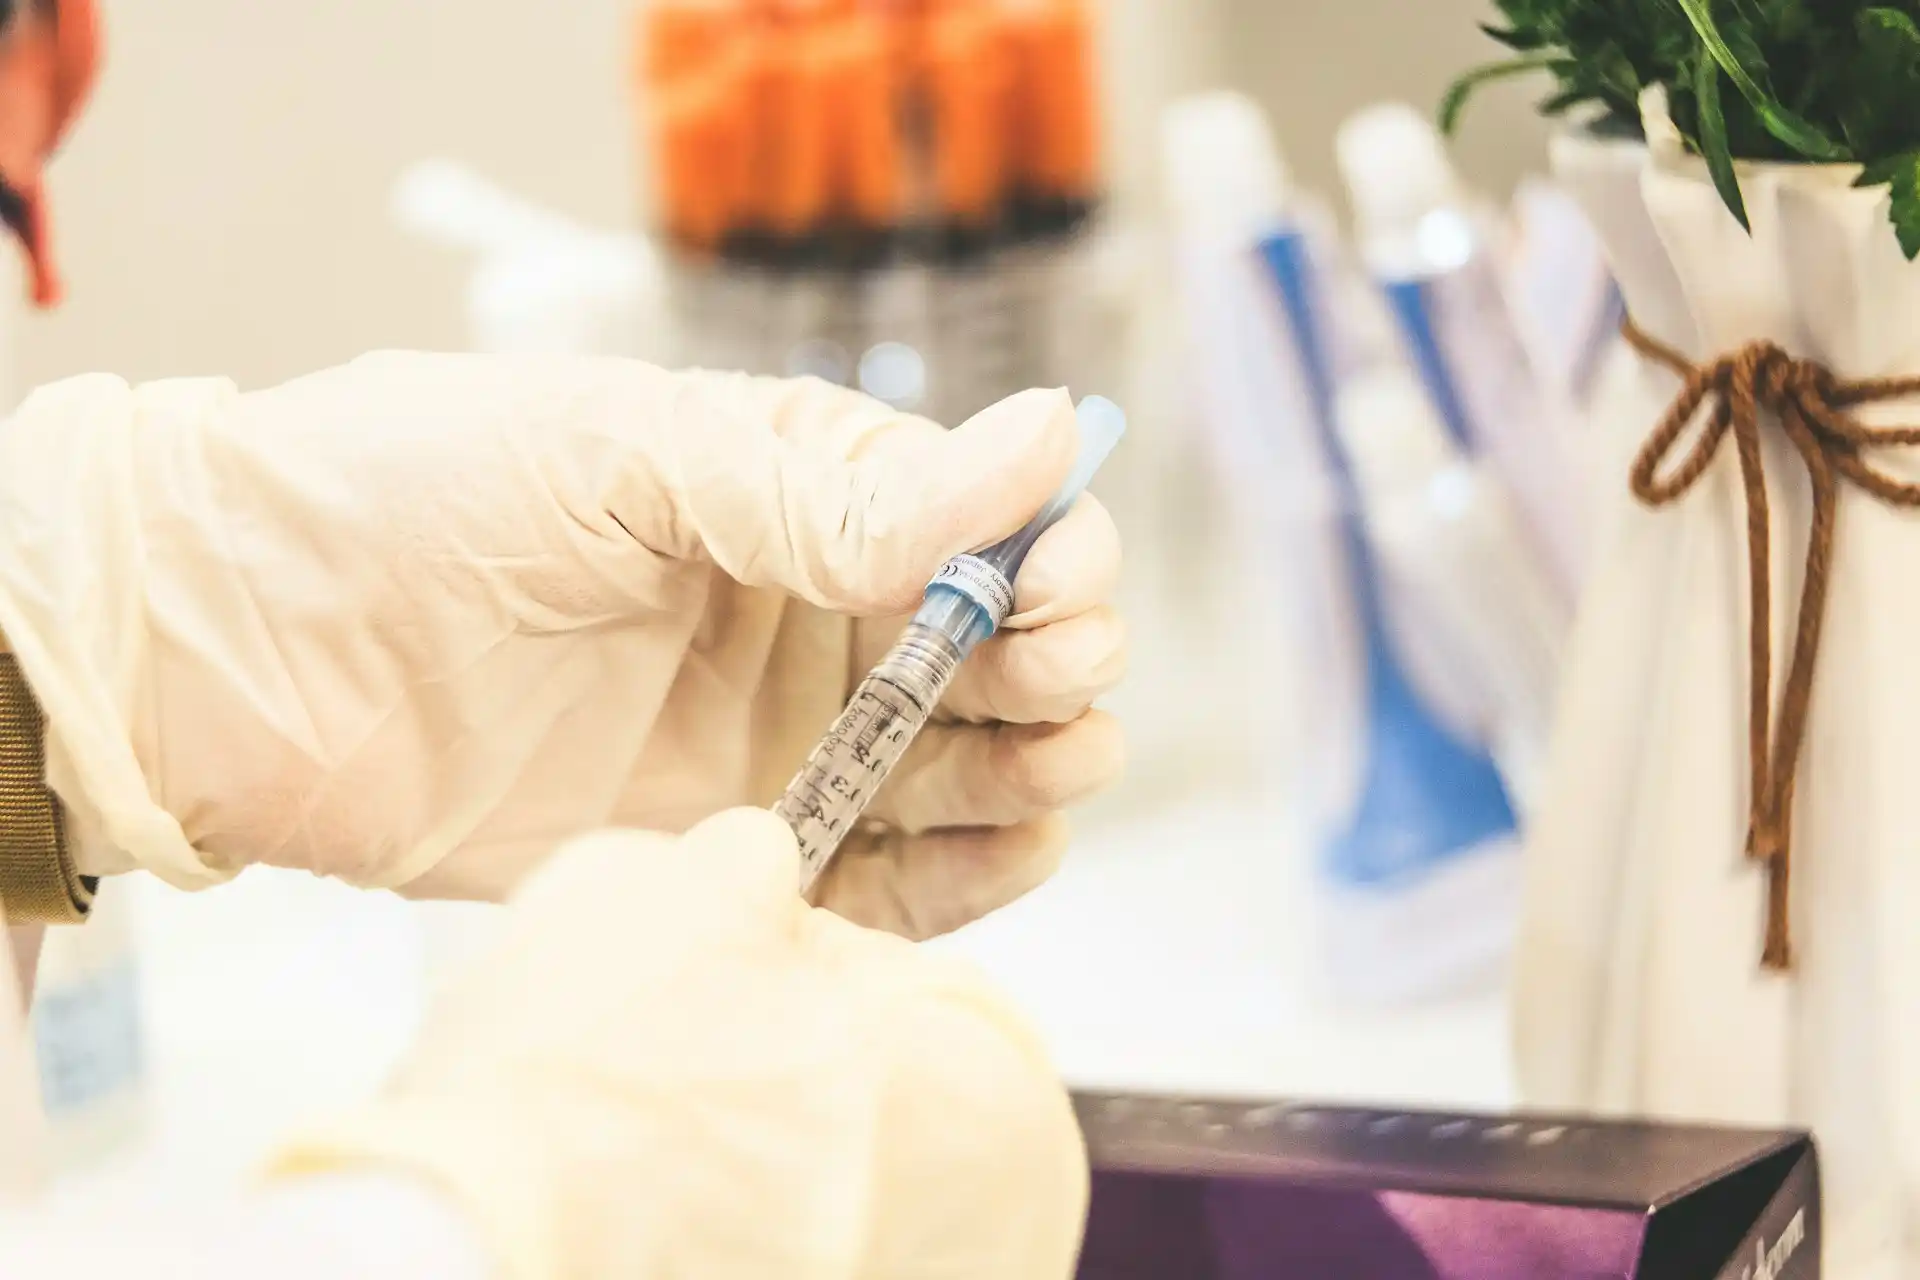
The trigger shot is given once your lead follicle reaches about 18 to 20 millimeters in diameter, with estradiol levels serving as a secondary indicator that the eggs are approaching maturity. It contains hCG or a GnRH agonist, and it prompts the final maturation and release of the egg, the same role it plays in other treatments like IVF.
Before this point, your body has been developing one or more follicles, either through your own cycle or with the help of medication if your cycle is stimulated. The trigger does not create that development; it sets the moment when the eggs inside those follicles finish maturing and are released, which is what makes the timing of insemination possible to plan around at all.
Ovidrel and Pregnyl are both hCG triggers commonly used ahead of IUI, and a GnRH agonist is sometimes used instead depending on your specific protocol. The choice between trigger types, along with how each one performs, is covered separately and is not repeated here, since that comparison belongs to its own detailed discussion rather than this timeline.
In a stimulated cycle, insemination is most commonly scheduled 34 to 36 hours after an hCG trigger, and clinics work anywhere in a 24 to 40 hour range depending on protocol. Ovulation itself usually follows 36 to 40 hours after the injection. Your clinic sets the exact hour from your monitoring.
Insemination is commonly scheduled between 24 and 36 hours after an hCG trigger, and many clinics work to a 34 to 36 hour standard, with practice across clinics spanning roughly 24 to 40 hours. Ovulation itself usually follows 36 to 40 hours after the injection. Your clinic sets the exact hour from your monitoring results, not from a fixed rule that applies the same way to everyone.
The reason for a range rather than one universal number is that ovulation timing after a trigger has some natural variation between patients, and clinics also differ somewhat in their own protocols and scheduling logistics. What matters for your specific cycle is the hour your own clinic sets, based on your own follicle size and hormone levels at the time of trigger.
This range applies to a stimulated, hCG-triggered cycle. In a natural cycle timed by your own LH surge, insemination is normally scheduled the next day, since the surge itself is the signal your clinic is tracking rather than an injection with a known interval. The two situations are governed by different biology, which is why they carry different scheduling logic entirely.

No. A randomized trial by Claman and colleagues in Fertility and Sterility in 2004 found the same pregnancy rates whether insemination happened 33 or 39 hours after hCG. A 2023 meta-analysis in Obstetrics and Gynecology likewise found no difference between hCG timed and LH timed insemination.
No, not meaningfully, and this is worth knowing if you are replaying the exact hour in your head right now. A randomized trial by Claman and colleagues, published in Fertility and Sterility in 2004, compared a short interval of 32 to 34 hours against a longer interval of 38 to 40 hours after hCG, in 189 total cycles, and found essentially the same pregnancy rate in both groups (20 pregnancies in 96 short-interval cycles versus 14 in 93 long-interval cycles, P = .398). That trial found no difference between the two intervals; it did not prove the two are perfectly equivalent, since a single trial of this size cannot rule out a small effect either way. But it is real evidence against the idea that a few hours makes or breaks a cycle.
A larger 2023 meta-analysis in Obstetrics and Gynecology reached a similar conclusion at a broader scale, finding no significant difference between insemination timed to hCG and insemination timed to a natural LH surge (OR 0.92, 95% CI 0.69 to 1.22, P = .53). And a 2025 update of the Cochrane systematic review on insemination timing (Cochrane Database of Systematic Reviews, CD006942, pub4) found the evidence insufficient to say that any one timing approach is safer or more effective than another. That is not the same statement as “timing does not matter.” It means the research has not found a difference worth acting on, which is a different and more honest claim. If you want to discuss how IUI timing may apply to your own cycle, you can speak with our fertility team.

Call your clinic. That is the first and most useful step, before anything else. Depending on how far off the timing is, teams commonly adjust the insemination hour, proceed as planned, or convert the cycle to timed intercourse if that fits the situation better. None of these is a failure state; they are the normal range of adjustments a monitored cycle is built to handle.
A missed or delayed trigger shot, or an LH surge that starts earlier than expected, are both situations your clinic has almost certainly managed before. What they do next depends on exactly how far off the timing is and what your monitoring shows at that point, which is why calling rather than guessing is the useful move. Some cycles proceed with a slight adjustment to the planned hour. Others are converted to a different approach for that attempt. Either way, the decision rests on your specific numbers, not on a general rule.
The evidence above is exactly why this range of adjustment exists. If a few hours reliably made the difference between success and failure, clinics would not have this flexibility built into how they handle a missed window, and the research on timing tolerance would look very different.
Several monitoring methods work together to set your specific timing, rather than any single measurement deciding it alone.
Your team looks at these together rather than relying on any one of them in isolation, since follicle size alone does not always tell the full story and hormone levels can vary somewhat between individuals. This combined picture is what lets your clinic set a specific trigger date rather than working from a generic calendar day.
Some patients also consider insemination on consecutive days to cover slight timing variation. This is a real approach some clinics use, worth raising directly with your care team if it is something you are curious about, since whether it fits your situation depends on your specific monitoring pattern and protocol.
We know every story is different and that taking the first step takes courage. Our medical team takes the time to assess your overall health and walk you through your options step by step, in a safe space and with complete transparency.
Trigger timing is one part of a monitored process, not a single moment you have to get exactly right on your own. Your care team is tracking the same signals described above and adjusting as your specific cycle responds, which is the entire point of monitoring in the first place, rather than leaving timing to a fixed calendar rule.
If you are mid-cycle and unsure whether something is off, the most useful step is the same one it always is: call your clinic and ask, rather than trying to work out on your own whether an hour here or there changed anything. Ready to plan your IUI? Talk through your cycle timeline and monitoring plan with our specialists.
The information in this article does not replace professional medical consultation. Every situation is different, and treatment decisions should be made with your care team based on your individual history and diagnosis.


Most IUI procedures are scheduled 24 to 36 hours after the trigger shot, with many clinics working to a 34 to 36 hour standard within that range. The exact hour depends on the type of trigger medication and your individual monitoring results.
Some individual variation exists, which is exactly why monitoring matters. If timing looks off in either direction, your clinic can usually adjust the plan rather than losing the cycle.
Contact your fertility clinic immediately. Depending on the timing, they may be able to give the injection late, adjust the insemination schedule, or convert the cycle to timed intercourse.
Once ovulation has already happened, the fertile window for that cycle is closing, and insemination timed after the fact is less likely to succeed than one timed beforehand, since the egg is only viable for a limited time after release. If monitoring shows this may have occurred, your clinic will talk through whether to proceed, adjust, or plan for the next cycle instead.
Follow your clinic’s specific instructions. In general, normal activity is fine, while avoiding intense exercise in the days around the procedure is a common precaution.
Injected hCG typically takes about 10 to 14 days to clear, which is part of why clinics time pregnancy testing carefully rather than relying on an early home test.



